Problem and constraints
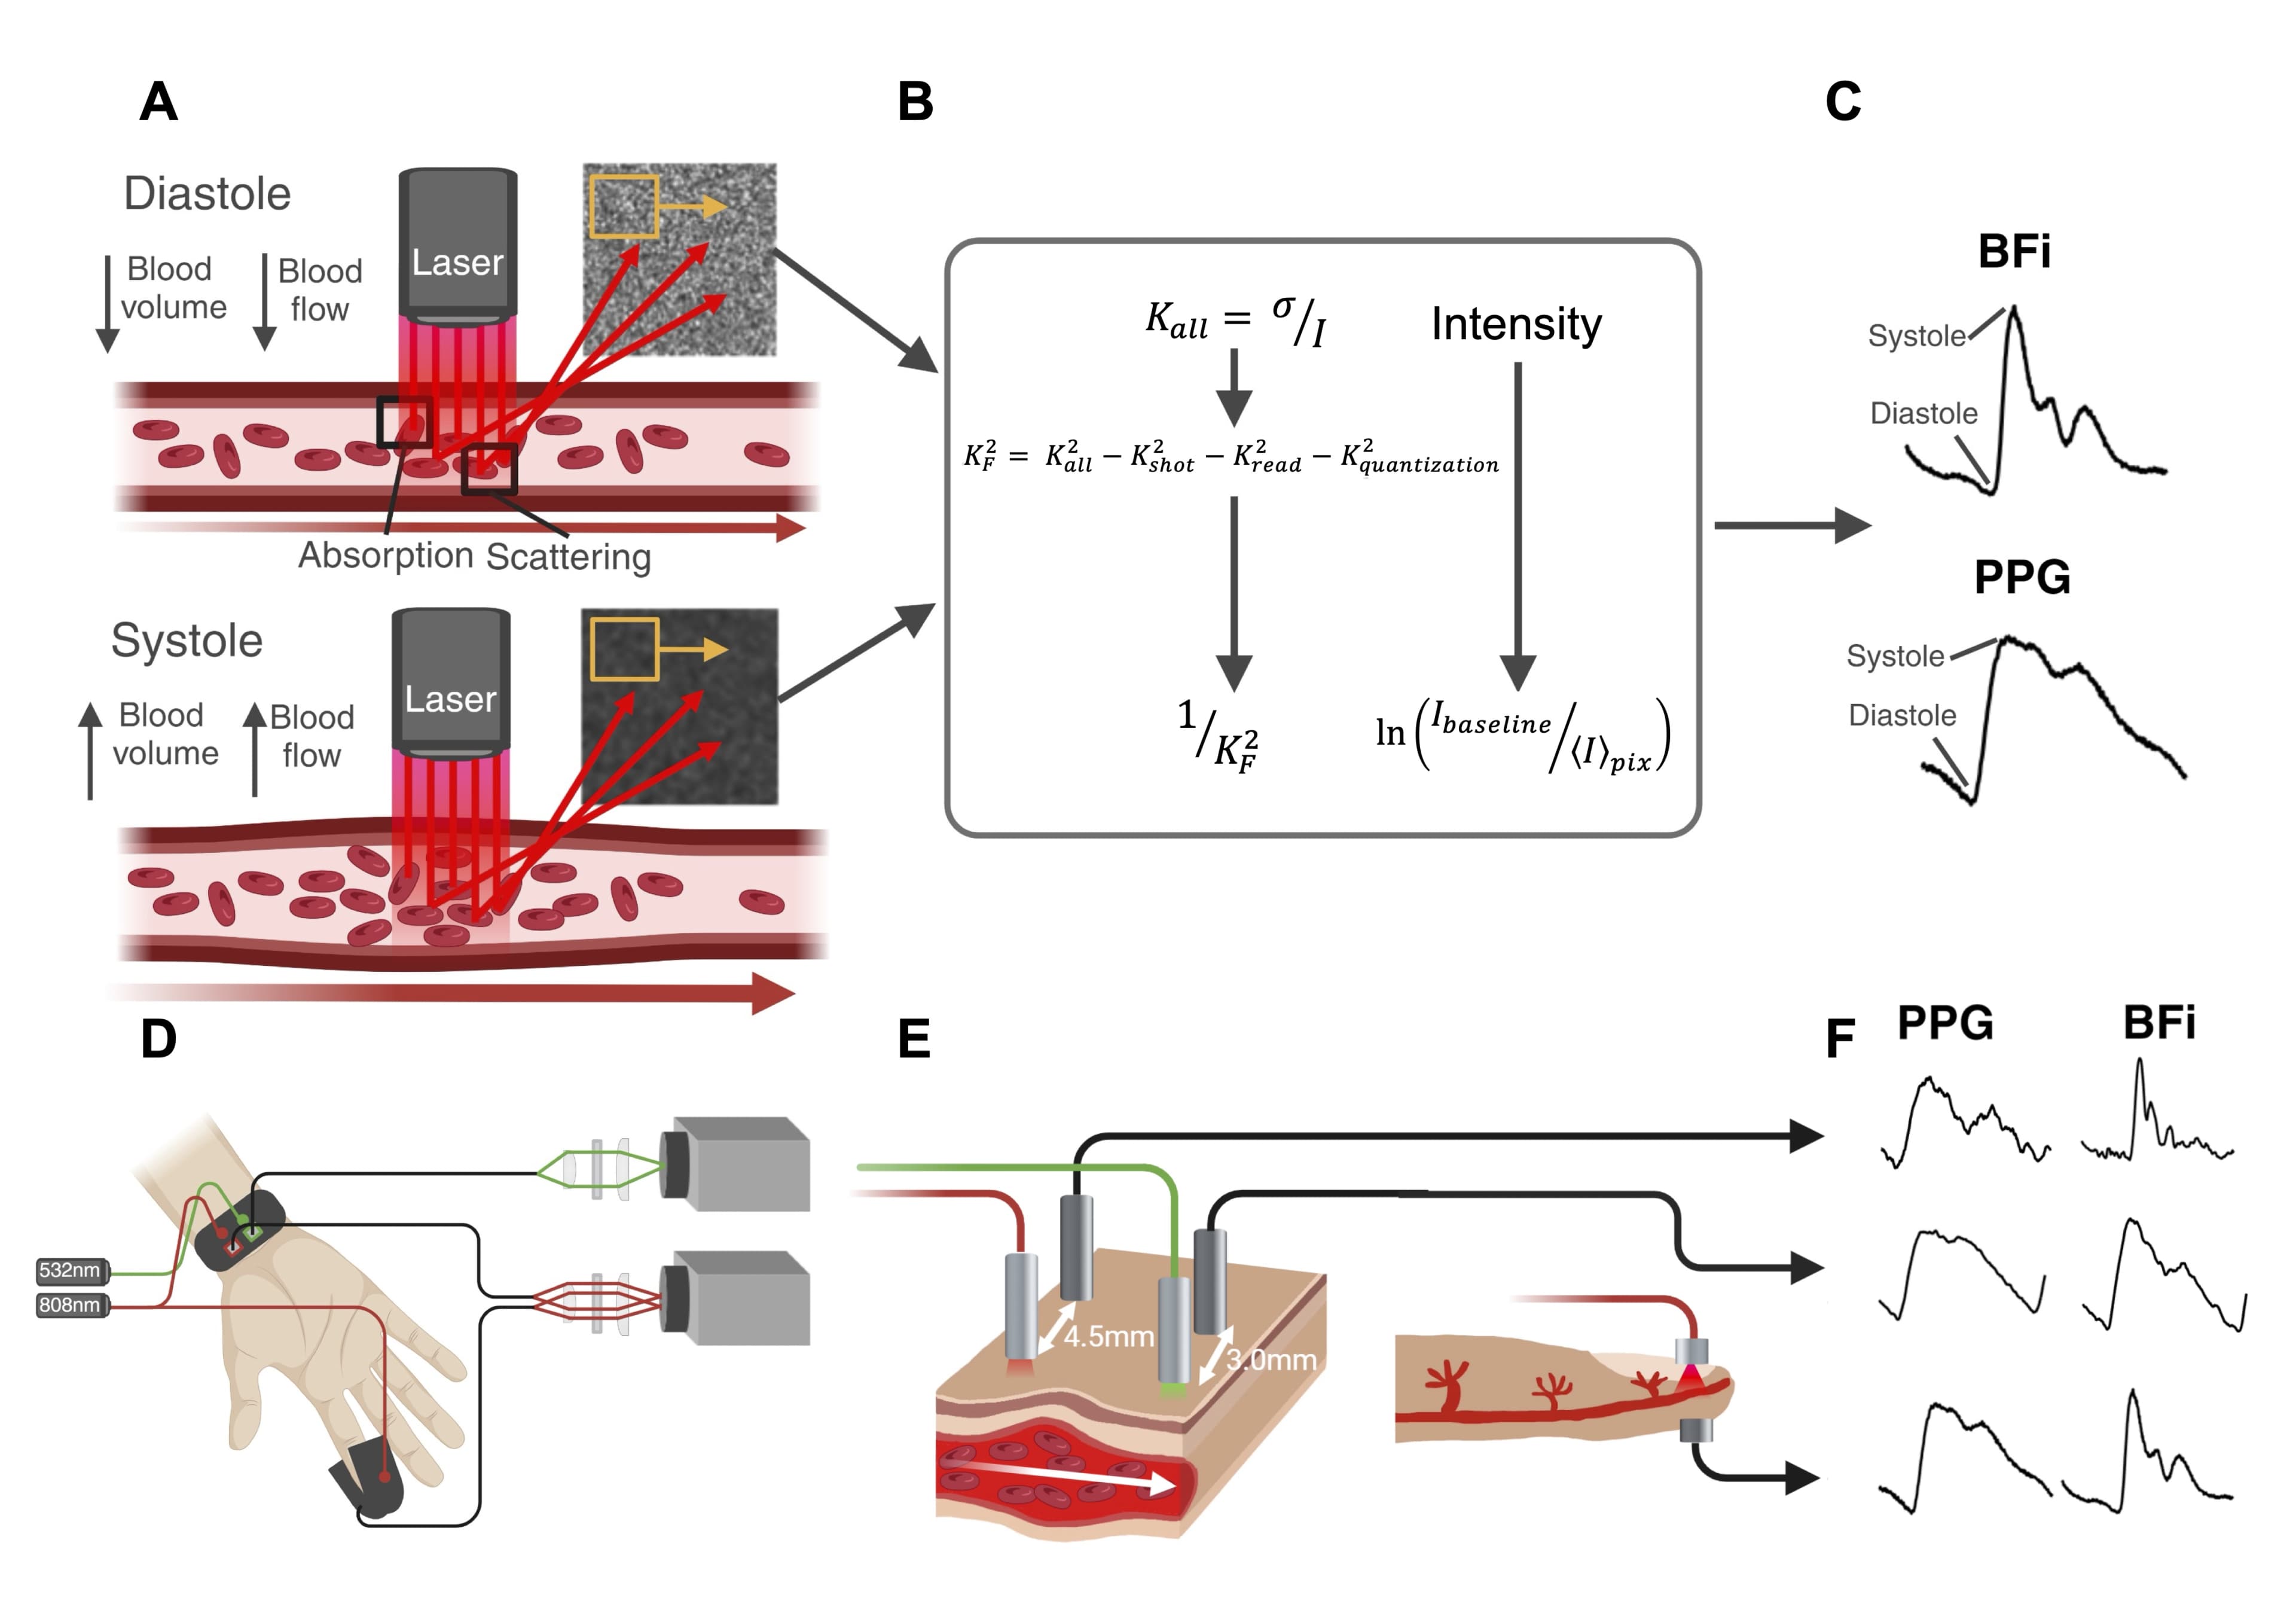
Cuffless blood-pressure estimation depends on useful optical measurements and a repeatable analysis workflow. Timothy's current experiment investigates positional signal-to-noise ratio, while his analytical work connects cardiac-waveform features to blood-pressure prediction and hypertension classification.
The experiment is IRB-supervised. Participant-level data is private, and this case study reports implemented methods without claiming clinically validated performance.
Timothy's role
Timothy leads measurement-protocol development, participant recruitment, measurements, and data analysis for the positional experiment. He also applies XGBoost to 80+ engineered cardiac-waveform features, analyzes hypertensive and non-hypertensive subjects, presents feature patterns, and develops wearable benchmark-test hardware.
Collaboration
Postdoctoral advisor Ariane Garrett provides research advisement and code support for an existing XGBoost workflow. Earlier dataset construction used raw scientific-trial data from studies Garrett ran. That earlier data provenance remains separate from the IRB-supervised positional experiment Timothy now leads.
Technical architecture and methods
Measurement protocol and dataset
Timothy creates and implements the protocol for positional signal-to-noise-ratio measurements and leads recruitment, measurement, and analysis. His earlier project-specific dataset organized advisor-run trial data for repeated analysis and clinical-cohort comparison.
Feature and modeling workflow
The analytical workflow uses 80+ engineered cardiac-waveform features. Timothy applies XGBoost to predict blood pressure and classify hypertension and analyzes feature patterns from hypertensive and non-hypertensive subjects.
The modeling builds on an existing XGBoost workflow adapted under Garrett's advisement and with advisor-assisted code.
Physical development
Timothy uses Autodesk Inventor and additive manufacturing to develop an attachable base for wireless wearable benchmark testing.
Engineering decisions and research constraints
The research connects experimental protocol development, traceable data preparation, cohort comparison, an established modeling workflow, and physical test hardware. Advisor support and earlier trial provenance remain part of the technical account.
Preliminary findings have been presented internally. No participant count, model-performance number, or clinical-validation result is asserted in this case study.